
What this is
- This research investigates the relationship between and biological aging in bipolar disorder (BD).
- It compares blood profiles of BD patients who respond to lithium treatment vs. those who do not, alongside nonpsychiatric controls.
- The study also explores biological aging through epigenetic and transcriptional age metrics.
Essence
- BD patients exhibit distinct patterns and accelerated biological aging compared to controls. Lithium responders show lower , suggesting potential protective effects.
Key takeaways
- 191 differentially methylated positions (DMPs) and 8 differentially methylated regions (DMRs) were identified in BD patients vs. controls. These alterations are linked to genes involved in postsynaptic density, relevant for synaptic plasticity.
- BD patients showed a higher biological age acceleration than controls using two epigenetic clocks (GrimAge and GrimAge2). This indicates that individuals with BD may experience accelerated aging.
- No significant differences in epigenetic aging were found based on lithium response; however, lithium responders exhibited lower age acceleration across all clocks, hinting at lithium's potential protective role.
Caveats
- The study's findings are based on peripheral blood samples, which may not fully represent central nervous system mechanisms. Future research should explore brain-specific methylation.
- The sample included only individuals of European descent, limiting the generalizability of the findings to other populations.
- The lack of significant DMPs associated with lithium response after correction for multiple testing may be due to the limited sample size and clinical variability.
Definitions
- DNA methylation: The addition of a methyl group to DNA, affecting gene expression without altering the DNA sequence.
- Epigenetic age acceleration: The difference between biological age estimated from epigenetic markers and chronological age, indicating faster biological aging.
- Transcriptional age acceleration: The difference between biological age estimated from gene expression data and chronological age, reflecting changes in cellular aging.
Simplified
Introduction
Bipolar disorder (BD) is a recurrent psychiatric disorder with a prevalence of more than 1% of the global population [1]. BD represents one of the leading causes of disability among young people, often characterized by functional impairment and reduced quality of life [1]. In addition, BD is associated with premature mortality compared to the general population, mainly due to increased prevalence of comorbid disorders associated with aging, such as cardiovascular and metabolic conditions [2]. Lithium is the gold standard for the long-term management of BD, due to its efficacy in the reduction of recurrences, as well as in its specific antisuicidal properties [3]. However, only one-third of patients show an excellent response to lithium, with the other two-thirds showing partial or no response [3]. Despite the extensive agreement among the international guidelines, which indicate lithium as first-line treatment for maintenance in BD [4], its use has been declining over the last decade [5]. The factors involved in the observed reduction in lithium prescription are complex to identify, but it is reasonable to assume that the narrow therapeutic window and its propensity to induce severe side effects have contributed significantly. On the other hand, because lithium-responsive BD patients return to well-being with levels of functioning and quality of life indistinguishable from those of healthy individuals, the search for biological markers of lithium response has been intense in the last few decades. Indeed, the identification of reliable biomarkers would allow for earlier identification of patients who would benefit most from lithium therapy, thereby reducing the risk of side effects and shortening the time needed for effective disease management.
Despite the growing body of molecular research on lithium response, and the findings supporting the heritability of lithium response [6], to date, clinical features seem to constitute the most robust factors to distinguish responders from nonresponders. Indeed, excellent responders represent a subtype of BD with distinct clinical features, such as familial loading for BD, episodic course of illness, and absence of rapid cycling [7]. Nevertheless, clinical characteristics have inherent limitations as orthogonal predictors of lithium response since some of these are time-dependent and volatile (clinical course) and might not be identifiable early in the course of the illness, or need reliable information from collaterals (family history), which need to be established accurately with detailed in-person assessments. In addition, clinical markers alone might not reach an adequate discriminative power to classify lithium responders versus nonresponders [8]. Thus, biological markers that are stable and less prone to variation over time are extremely relevant in increasing the accuracy of predictive models of lithium response, especially if integrated with clinical data.
A large body of research has tried to elucidate the genetic architecture of lithium response. However, this research has been hampered by the multiple pharmacodynamic effects of lithium that make it hard to understand which molecular mechanism underlies its clinical efficacy [3]. Both BD and lithium response are multifactorial phenotypes resulting from an interaction between genetic predisposition and environmental factors. Accordingly, genetic variants can only explain a small proportion of the interindividual variability in these phenotypes. Epigenetic mechanisms dynamically modulate gene expression in response to environmental stimuli and, therefore, represent promising candidates to account for at least part of this missing heritability [9]. In particular, DNA methylation, that is, the transfer of a methyl group to the C5 position of a cytosine to form 5-methylcytosine, is one of the most studied epigenetic mechanisms, being the most stable form of epigenetic alteration [10].
Differences in global methylation [11], in the methylation status of candidate genes [12], or in genome-wide DNA methylation patterns [13] have been previously implicated in BD and in lithium response [14]. Marie-Claire et al. used a genome-wide approach (SeqCapEpi) and identified seven differentially methylated regions (DMRs) discriminating responders and nonresponders [15], three of which were subsequently validated with methylation-specific high-resolution melting in an extended sample [16]. A more recent study including 26 excellent responders and 27 nonresponders to lithium identified 130 differentially methylated positions (DMPs) and 16 DMRs between the two groups, with some of the identified genes previously implicated in lithium response [17].
Whole-genome methylation also enables the estimation of epigenetic age through epigenetic clocks. This is relevant since a large body of evidence suggests BD to be characterized by accelerated aging, a condition in which biological aging occurs at a faster rate than chronological aging [18]. Indeed, BD is characterized by decreased life expectancy (up to 10–20 years compared to the general population) and patients may show alterations of biological markers of cellular aging, such as shorter telomere length, altered mitochondrial DNA copy number, and increased brain age [18]. Some studies reported longer telomere length in patients treated with lithium compared with patients not treated with this drug or controls, or a positive correlation between telomere length and years of lithium treatment, supporting the hypothesis of a protective effect of lithium against accelerated aging [19-24]. Nonetheless, previous studies estimating epigenetic age in patients with BD, or the potential effect of pharmacological treatment, provided contrasting results. Two studies found no evidence of differences in epigenetic age acceleration in patients with BD compared with controls in lymphoblastoid cell lines [25] or in whole blood from lithium responders compared with nonresponders [17]. Conversely, another study showed epigenetic age deceleration in BD patients compared with controls, as well as in BD patients treated with combinations of mood stabilizers (including lithium, valproate, and carbamazepine) compared with patients taking no medication or treated in monotherapy [26]. Biological age can also be estimated through transcriptomics data, with this measure suggested to offer complementary information compared to epigenetic age [27]. However, to date, no study has explored transcriptional age in patients with BD.
In this study, we aimed to identify genome-wide methylation signatures differentiating (1) patients with BD and controls; and (2) patients with BD characterized as responders and nonresponders to long-term lithium treatment using a validated scale. In addition, we estimated epigenetic and transcriptional age to compare these groups in terms of biological age acceleration.
Methods
Sample
| Variable | Patients with BD ( = 64)n | Controls ( = 32)n | Statistics | p |
|---|---|---|---|---|
| Age, mean years (SD) | 54.13 (13.58) | 53.38 (7.40) | = 883U | 0.27 |
| Sex (F/M) | 41/23 | 18/14 | = 0.55χ2 | 0.51 |
| BMI, mean (SD) | 26.65 (4.33) | 23.88 (4.14) | = 2.90t | 0.005 |
Methylation assessment and quality control
Genomic DNA was extracted from whole blood using the salting-out method [30]. A total of 500 ng of genomic DNA was bisulfite-converted using the EZ DNA Methylation-Lightning Kit (Zymo Research). Genome-wide DNA methylation was measured with the Infinium Methylation EPIC v2.0 arrays (Illumina, San Diego, CA, USA) using an iScan system (Illumina) at the Centre for Research University Services (CeSAR) of the University of Cagliari. Preprocessing of IDAT files was conducted using the minfi [31] and the ChAMP packages [32] in R. Quality control included removal of probes with detection p-value <10e-16, with a bead count < 3 in at least 5% of samples, non-CpG probes, single-nucleotide polymorphisms-related probes, and probes located on X,Y chromosomes. Replicate probes were averaged with the DMRcate R package [33]. After quality control, analyses included 781,602 probes and 96 participants. Visual inspection of multidimensional scaling plots and of type-I and type-II density plots was conducted before and after Beta-Mixture Quantile normalization. The singular value decomposition (SVD) method was used to assess the association between the main sources of variation and the top principal components (PCs). Batch effect correction for the slide was conducted with the ComBat normalization method in ChAMP. Smoking was estimated based on M values of the cg05575921 probe, while cell type proportions were estimated using the Houseman algorithm [34].
Analysis of differentially methylated probes and functional enrichment
We assessed DMPs between patients with BD and controls using general linear models implemented in limma [35] adjusting for sex, age, estimated smoking, the first five cell type proportions PCs, and the top five control probes PCs. Models assessing DMPs between lithium responders and nonresponders were adjusted for sex, age, estimated smoking, the first five cell type proportions PCs, and lithium treatment at recruitment. Covariates were selected due to their suggested effect on methylation profiles in previous studies or their association with methylation values on the first PCs in the SVD plot. Upstream regulators of significant DMPs were identified with Ingenuity Pathway Analysis (IPA) [36]. The blood–brain correlation of significant CpGs was tested with the BECon tool [37]. DMRs between groups were assessed with DMRcate [33]. P-values were computed based on Stouffer's method and adjusted for multiple testing based on the Benjamini–Hochberg false discovery rate (FDR) procedure. [33]. Functional enrichment for Reactome pathways and Gene Ontology (GO) terms of genes in which DMPs and DMRs were located was conducted with enrichR [38] with default settings. For all analyses, results were adjusted for multiple testing based on FDR, and an adjusted p < 0.05 was considered to be significant.
Analysis of epigenetic age acceleration
Five epigenetic clocks (Horvath1, Hannum, PhenoAge, GrimAge, and GrimAge2) and their respective epigenetic age acceleration values (i.e., the residual from regressing epigenetic age on chronological age) were computed with the DNA Methylation Age Calculator web portal [39, 40]. A positive epigenetic age acceleration indicates a higher epigenetic age compared to chronological age. Normality of distribution was tested with the Shapiro–Wilk test, and the correlation between epigenetic clocks or epigenetic age acceleration clinical variables was computed with Pearson's or Spearman's correlation test, based on the distribution of the tested variables, or with a zero-inflated Poisson model in the case of the Alda scale TS. Epigenetic age acceleration was used for all subsequent analyses. Two outliers for GrimAge and GrimAge2 epigenetic acceleration identified with Grubb's test were removed. Unadjusted differences in epigenetic age acceleration between patients with BD and controls or lithium responders and nonresponders were tested with Student's t-test or Mann–Whitney U test, based on the distribution. Since epigenetic acceleration based on the GrimAge and the GrimAge2 clocks showed a significant difference between patients and controls, its association with covariates was tested with Mann–Whitney U test (sex, BD subtype, and treatment with lithium at blood draw) or Spearman's correlation test (quantitative variables). Analyses adjusted for variables showing a significant association with epigenetic age acceleration (sex) or potential confounders (chronological age and BMI) were conducted using Quade nonparametric analysis of covariance. Finally, we computed DunedinPACE, which is a blood DNA methylation biomarker of the pace of biological aging. Based on methylation levels of 173 CpG sites, DunedinPACE quantifies the pace of aging of an individual (i.e., the number of biological years aged in comparison to one chronological year of aging) [41]. Values >1 represent a faster pace of aging. We tested the unadjusted association between DunedinPACE and categorical or quantitative variables using Student's t-test or Pearson's correlation test, respectively. In addition, we tested the association between DunedinPACE and BD diagnosis using a binary logistic regression model with BD diagnosis as the outcome, and sex, chronological age, and BMI as predictors.
Analysis of transcriptional age acceleration
Library preparation and bulk RNA sequencing were performed at CeSAR (University of Cagliari). Total RNA was extracted from 2.5 mL of blood with the PAXGene Blood miRNA Kit (Qiagen). RNA quality was evaluated using an RNA ScreenTape system (Agilent), and all samples had an RNA integrity number value ≥7. RNA samples were processed using the Illumina Stranded Total RNA Prep with Ribo-Zero Plus kit, and paired-end sequencing (2 × 150 bp) was performed on a NextSeq 2000 platform (Illumina). After quality control performed with FASTQC and MULTIQC, raw data were processed with the rnaseq nf-core pipeline [42]. Alignment with the reference genome (GRCh38) was performed with STAR [43], while gene expression levels were estimated with RSEM [44]. Normalized counts were used as input to compute transcriptional age with the RNAAgeCalc tissue-specific method [27]. This method was developed through the identification of age-related genes in the GTEx database and allows for computing transcriptional age acceleration (computed as the residuals from regressing transcriptional age on chronological age) in a tissue-specific way. A positive transcriptional age acceleration indicates higher transcriptional age compared to chronological age. The presence of outliers was checked with Grubb's test, and no outliers were identified. The correlation between transcriptional age and chronological age was tested with Pearson's correlation test or with a zero-inflated Poisson model in the case of the Alda scale TS. Unadjusted differences in transcriptional age acceleration between patients with BD and controls, or between lithium responders and nonresponders, were tested with Student's t-test. The association between transcriptional age acceleration and covariates was tested with Student's t-test or Pearson's correlation test.
Results
Association between whole-blood methylation profiles and BD or lithium response

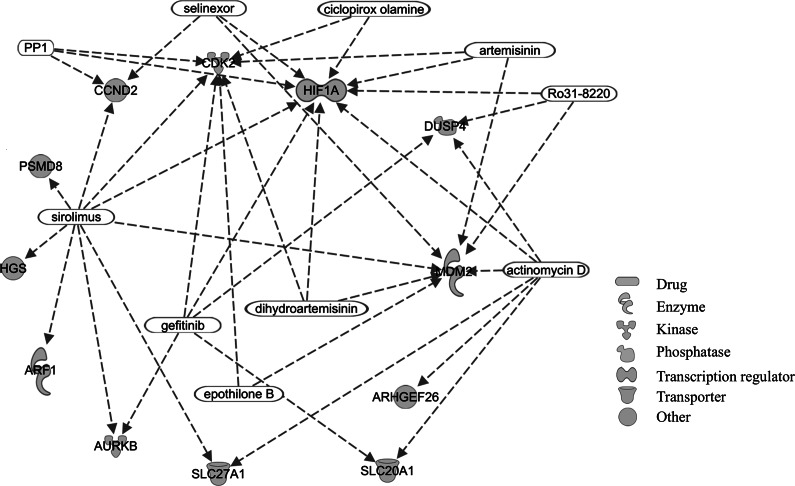
Network of drugs acting as significant upstream regulators of genes associated with bipolar disorder.
| ID | Chr | Start | End | N.cpgs | FDR | Meandiff | Overlapping genes |
|---|---|---|---|---|---|---|---|
| DMR1 | 16 | 56961901 | 56961944 | 3 | 0.009 | 0.06 | CETP |
| DMR2 | 17 | 48603455 | 48605418 | 15 | 0.019 | −0.09 | HOXB-AS3, HOXB3, HOXB6 |
| DMR3 | 10 | 34636101 | 34636712 | 3 | 0.023 | −0.04 | PARD3 |
| DMR4 | 1 | 226549544 | 226549640 | 2 | 0.03 | 0.01 | STUM |
| DMR5 | 12 | 54369427 | 54369649 | 3 | 0.035 | 0.07 | AC079313.2, AC079313.1, ZNF385A |
| DMR6 | 2 | 27306672 | 27306920 | 2 | 0.039 | 0.02 | TRIM54 |
| DMR7 | 3 | 308820 | 309320 | 6 | 0.041 | −0.06 | CHL1, RPS8P6 |
| DMR8 | 7 | 74656163 | 74656567 | 2 | 0.043 | −0.01 | GTF2I |
| Probe | Chr | BP | logFC | t | p | FDR | Gene | Feature | Cgi |
|---|---|---|---|---|---|---|---|---|---|
| cg13259408 | 10 | 34636101 | −0.44 | −7.30 | 1.55E–10 | 0.0001 | OpenSea | ||
| cg23550779 | 12 | 29372422 | −0.74 | −6.98 | 6.45E–10 | 0.0003 | OpenSea | ||
| cg04948941 | 14 | 61695160 | 0.26 | 6.31 | 1.30E–08 | 0.0032 | HIF1A | TSS1500 | Island |
| cg08836736 | 11 | 30424053 | −0.37 | −6.25 | 1.66E–08 | 0.0032 | OpenSea | ||
| cg01636258 | 4 | 80615269 | −0.49 | −6.17 | 2.38E–08 | 0.0035 | OpenSea | ||
| cg26797661 | 1 | 151166040 | 0.26 | 6.14 | 2.69E–08 | 0.0035 | SCNM1 | TSS200 | OpenSea |
| cg24395955 | 19 | 32362571 | −1.29 | −6.07 | 3.62E–08 | 0.004 | OpenSea | ||
| cg10120645 | 8 | 124474394 | 0.35 | 5.91 | 7.12E–08 | 0.0069 | RNF139-DT | Exon | Island |
| cg20335273 | 13 | 51623731 | 0.6 | 5.89 | 7.90E–08 | 0.0069 | OpenSea | ||
| cg11265407 | 7 | 80541942 | −0.41 | −5.86 | 9.02E–08 | 0.0071 | OpenSea | ||
| cg01173986 | 1 | 62596297 | −0.59 | −5.76 | 1.39E–07 | 0.0093 | ANGPTL3 | TSS1500 | OpenSea |
| cg02771392 | 7 | 64902704 | −0.40 | −5.75 | 1.43E–07 | 0.0093 | ZNF273 | TSS1500 | OpenSea |
| cg25102879 | 10 | 95168442 | −0.47 | −5.71 | 1.69E–07 | 0.0096 | OpenSea | ||
| cg00244474 | 1 | 12268366 | −0.33 | −5.69 | 1.82E–07 | 0.0096 | OpenSea | ||
| cg24402392 | 11 | 123198430 | −0.41 | −5.69 | 1.85E–07 | 0.0096 | Shelf | ||
| cg13236968 | 8 | 61454112 | 0.57 | 5.67 | 1.96E–07 | 0.0096 | OpenSea | ||
| cg25744017 | 15 | 52527127 | −0.26 | −5.61 | 2.62E–07 | 0.0121 | Shore | ||
| cg23989618 | 19 | 4992235 | −0.85 | −5.59 | 2.80E–07 | 0.0122 | OpenSea | ||
| cg16667784 | 11 | 78257237 | −0.34 | −5.51 | 3.94E–07 | 0.0143 | OpenSea | ||
| cg23668004 | 7 | 4745272 | 0.29 | 5.51 | 3.95E–07 | 0.0143 | Island | ||
| cg18608814 | 8 | 51617923 | −0.49 | −5.51 | 3.96E–07 | 0.0143 | OpenSea | ||
| cg07914296 | 2 | 188296928 | −0.51 | −5.50 | 4.02E–07 | 0.0143 | MIR561 | TSS1500 | Shelf |
| cg25568561 | 14 | 101809750 | 0.48 | 5.47 | 4.60E–07 | 0.0146 | PPP2R5C | TSS200 | OpenSea |
| cg08105772 | 18 | 74267042 | −0.38 | −5.46 | 4.84E–07 | 0.0146 | OpenSea | ||
| cg14519123 | 15 | 66252627 | 0.25 | 5.46 | 4.86E–07 | 0.0146 | Island | ||
| cg11921411 | 3 | 61965316 | −0.76 | −5.45 | 4.91E–07 | 0.0146 | OpenSea | ||
| cg25216443 | 2 | 177771466 | −0.84 | −5.43 | 5.40E–07 | 0.0146 | OpenSea | ||
| cg16705351 | 1 | 226549544 | 0.33 | 5.43 | 5.47E–07 | 0.0146 | Island | ||
| cg02996269 | 4 | 105473535 | 0.19 | 5.43 | 5.49E–07 | 0.0146 | Island | ||
| cg24217756 | 3 | 180989722 | 0.47 | 5.42 | 5.61E–07 | 0.0146 | DNAJC19 | 5UTR | Island |
| Term | Description | P | FDR | Odds ratio | Genes |
|---|---|---|---|---|---|
| Reactome pathways | |||||
| R-HSA–69563 | p53-dependent G1 DNA damage response | 0.0001 | 0.03 | 17.24 | PSMD8, CDK2, MDM2, ZNF385A |
| R-HSA–69580 | p53-dependent G1 S DNA damage checkpoint | 0.0001 | 0.03 | 17.24 | PSMD8, CDK2, MDM2, ZNF385A |
| R-HSA–69615 | G1 S DNA damage checkpoints | 0.0002 | 0.03 | 16.56 | PSMD8, CDK2, MDM2, ZNF385A |
| GO cellular component | |||||
| GO:1902554 | Serine/threonine protein kinase complex | 0.0004 | 0.04 | 12.41 | CCNJ, CCND2, PARD3, CDK2 |
| SynGO 2024 | |||||
| GO:0014069 | Postsynaptic density | 0.0012 | 0.01 | 6.81 | ARF1, RPS6KC1, MDM2, PIP5K1C, PHB2 |
| GO:0099149 | Regulation of postsynaptic Neurotransmitter Receptor Endocytosis | 0.0012 | 0.01 | 15.68 | MDM2, PIP5K1C, PACSIN1 |
Differences in epigenetic age acceleration
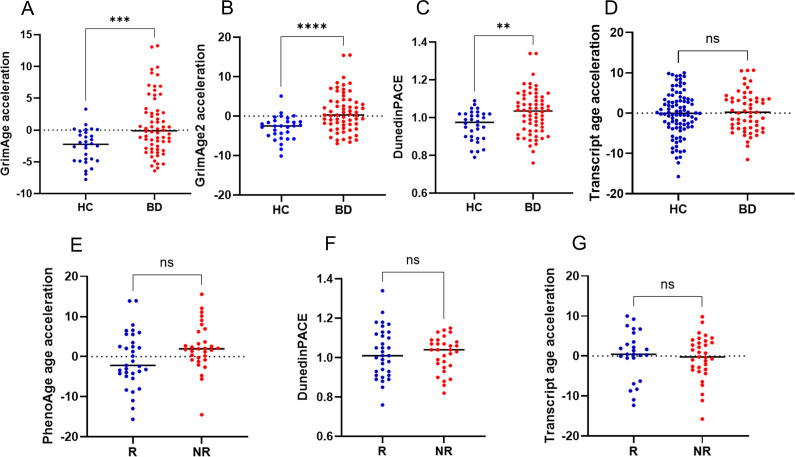
In addition, patients with BD showed a faster pace of aging based on DunedinPACE compared with controls (BD: 1.03, controls: 0.96, t = 3.01, p = 0.003, Figure 2). The pace of aging was significantly positively correlated with BMI (Pearson's correlation coefficient = 0.30, p = 0.005) and not significantly associated with other variables (Supplementary Table 9↗). The association between BD and DunedinPACE was significant also in a binary logistic regression model (R2 di Nagelkerke = 0.26, p of the model 0.006, DunedinPACE p = 0.029) adjusted for sex (0.023), chronological age (0.22), and BMI (p = 0.006). We observed no significant difference in the pace of aging measured with DunedinPACE based on lithium response (t = −0.24, p = 0.81).

Differences in epigenetic and transcriptional age acceleration between BD and controls or between lithium responders and nonresponders. The upper part of the figure shows differences between patients with BD and controls in (A) epigenetic age acceleration using the GrimAge or (B) the GrimAge2 epigenetic clock, (C) DunedinPACE, and (D) transcriptional age acceleration; the lower part of the figure shows differences between lithium responders and nonresponders in (E) epigenetic age acceleration using the phenoAge epigenetic clock, (F) DunedinPACE, and (G) transcriptional age acceleration. BD, bipolar disorder; HC, healthy controls; NR, nonresponders; ns, not significant; R, responders.
Differences in transcriptional age acceleration
Transcriptional age was positively correlated with chronological age (Pearson's correlation coefficient = 0.60, p = 0.001) and with epigenetic age using all clocks, while only a trend for positive correlation was observed for the pace of aging estimated with DunedinPACE (Supplementary Table 10↗). However, we did not find a significant difference based on BD diagnosis (t = 0.61, p = 0.54) or lithium response (t = 0.45, p = 0.66). Transcriptional age acceleration was not associated with other clinical variables (Supplementary Table 11↗).
Discussion
This study investigated genome-wide peripheral blood DNA methylation patterns and epigenetic and transcriptional age acceleration in individuals with BD compared to nonpsychiatric controls, and explored differences based on lithium response within the BD group. Our findings showed significant alterations in DNA methylation in BD patients compared to controls, providing novel insights into the molecular underpinnings of this complex mental disorder. Moreover, they further support the evidence that BD might be associated with accelerated aging.
The set of DMPs and DMRs associated with BD was enriched for different pathways and GO terms, among which two were related to postsynaptic density, an electron-dense structure containing a high concentration of scaffolding, adaptor, and signaling proteins, adjacent to the postsynaptic membrane of excitatory synapses [45, 46]. This macromolecular complex is involved in several functions, including dopamine and glutamate-dependent synaptic plasticity processes at excitatory synapses [47]. Genes involved in postsynaptic density have been implicated in the pathophysiology of BD by a study integrating brain transcriptome data from postmortem dorsolateral prefrontal cortex and genome-wide association (GWA) signals [48]. Using weighted gene co-expression network analysis, the authors found that modules including genes differentially expressed in BD and with signals in prior GWA of BD were enriched for genes involved in postsynaptic density, strongly supporting the hypothesis that dysregulation of this structure might be involved in the pathogenesis of BD.
Using IPA, we identified a network of upstream regulators of genes including DMPs significantly associated with BD (Supplementary Table 3↗). Chemical compounds in the network included artemisinin and its derivative dihydroartemisinin (Figure 1 and Supplementary Table 3↗). Artemisinin is a natural antimalarial compound obtained from the Artemisia annua plant. Artemisin and dihydroartemisinin are currently being investigated in autoimmune disorders due to their potential immunomodulatory effects [49, 50]. In addition, artemisinin has been found to be able to suppress neuroinflammation and promote synaptic plasticity in rats subjected to single prolonged stress [51], and dihydroartemisinin to exert antidepressant effects in chronic unpredictable mild stress-induced mice [52]. These compounds were found to be upstream regulators of three genes differentially methylated in our data, two of which were hypermethylated (CDK2 and HIF1A) and one hypomethylated (MDM2) in patients with BD compared with controls (Supplementary Tables 2↗ and 3↗). While the potential repurposing properties of artemisinin in psychiatric disorders have just started to be explored in preclinical models, our results support its potential role as a regulator of genes differentially methylated in patients with BD compared with controls.
While we did not identify DMPs significantly associated with lithium response after multiple testing correction, several genes including DMPs identified by Zafrilla-Lopez et al. (hypermethylated in responders: ABI2, ALK, B4GALNT3, CACNA2D2, CD19, CNIH3, HP1BP3, KCNQ5, NEUROD4, NHSL1, PSME3, RIMBP2, SLC45A2, SYTL3, TENM2, TEP1, THSD7A, ZC3H4, and ZNHIT3; or hypomethylated in responders: ADAMTS12, PDE2A, RGS10, TMEM177, TMEM201, TRAF3IP2-AS1, and ZNF205) [17] or a DMR identified by Marie-Claire et al. (EIF2B5) [15], showed nominal significance in our results (Supplementary Table 5↗). While the lack of significance after multiple testing correction might be explained by several factors, including the limited sample size, clinical heterogeneity, as well as the methods used to measure methylation compared with previous studies, the nominal significance of a large number of targets with the same direction of effect supports the hypothesis of a role of epigenetic mechanisms in lithium response.
We observed higher epigenetic age acceleration and pace of aging, but not transcriptional age acceleration, in patients with BD compared with controls. Premature senescence has been largely supported in BD, based on studies suggesting a higher risk of developing dementia [53], premature death [54, 55], accelerated deterioration in executive functions and cognitive regulation [56], comorbid medical conditions typically associated with aging [57], and a faster rate of brain aging [58, 59]. In terms of molecular findings, several studies reported signatures of accelerated biological aging in BD, such as shorter telomere length and altered telomere dynamics [21], accelerated brain aging in imaging studies [60], increased inflammation and oxidative stress [61], altered DNA mitochondrial copy number [62, 63], genetically determined aging markers [64], as well as accelerated epigenetic age [65]. For the first time, we investigated increased transcriptional age acceleration in patients with BD compared with controls. While transcriptional age has only recently started to be explored in psychiatric disorders, due to the relative paucity of suitable methods and of transcriptome data, this measure has been suggested to offer complementary information to DNA methylation age in the analysis of mortality risk across different types of cancer [27]. This method has recently allowed for determining higher biological age in individuals with post-traumatic stress disorder (PTSD) in blood [66] as well as individuals with PTSD or major depressive disorder in post-mortem brain samples from the ventromedial prefrontal cortex, compared to controls [67]. To our knowledge, our study is the first to compute transcriptional age in BD, thus contributing valuable data that supports the exploration of biological aging in mental illness through alternative and complementary methods. While we observed no significant difference in epigenetic aging based on lithium response, in line with a previous study [17], lithium responders showed lower epigenetic acceleration using all clocks, with a trend more evident using the PhenoAge epigenetic clock (t = 1.97, p = 0.053). While this trend has to be interpreted cautiously, it is in line with the hypothesis that lithium might exert protective properties against accelerated cellular aging in patients with BD [68].
Strengths of our study include the use of a validated scale to characterize lithium response and the use of two complementary measures of biological aging. However, our results should be interpreted considering some limitations. Whole genome methylation analysis and bulk RNA sequencing were conducted on whole blood DNA and RNA. We found a significant enrichment for the "postsynaptic density" and "Regulation of postsynaptic neurotransmitter receptor endocytosis" SynGO terms, as well as a subset of DMPs in the highest percentiles of brain–blood correlation based on BECon, suggesting a potential brain relevance for at least some of the identified targets. However, while the access to brain DNA methylation and RNA expression remains difficult, studies on neural precursors or differentiated neurons from induced pluripotent stem cells might allow us to elucidate whether our results might be relevant for central mechanisms or rather be limited to the identification of peripheral biomarkers of diagnosis and clinical response. In addition, this study only included participants of European origin. Therefore, the extent to which results might be extended to different populations has not been explored. Finally, we did not validate targets identified by previous studies investigating genome-wide methylation in patients with BD characterized for lithium response. Although various factors may have contributed to the lack of replication (e.g., variability in experimental design or differences in clinical recruitment procedures across studies), one key factor could be the limited sample size after stratification by lithium response – even though this is consistent with previous studies [15, 17].
In conclusion, our results point to different peripheral methylation profiles associated with BD and support the hypothesis of accelerated aging in BD. Moreover, pathway analysis of identified targets suggested that some of the DMPs are targeted by natural compounds with immunomodulatory and antidepressant effects, thus potentially supporting drug repurposing strategies for a more effective management of BD.